To receive a free PDF copy of The Fundamentals of Electrocardiograph Interpretation by Harry Mond, subscribe to his email blog by entering your email address below.
Thank you! Your submission has been received!
Oops! Something went wrong while submitting the form.
Purchase the textbook
Purchase a hard cover or paperback copy of The Fundamentals of Electrocardiograph Interpretation by Harry Mond on Amazon.
I was asked for a second opinion on this Holter study as there was confusion with different QRS configurations and rhythms. I selected a bunch of strips.
What do you think? Again arrows and highlight help.
Let us start at the top.
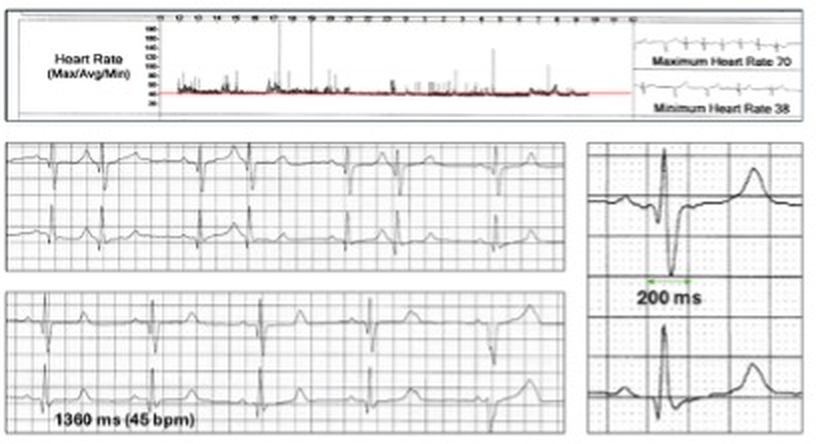
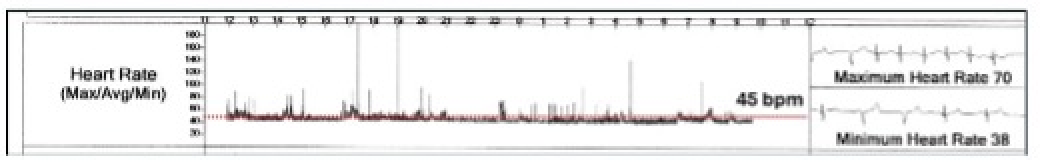
24-hour rate histogram
Significant bradycardia with a mean heart rate of about 45 bpm and maximum 70 bpm. The rate response to daytime exertion is very poor and there are a few narrow spikes probably due to premature ectopics.
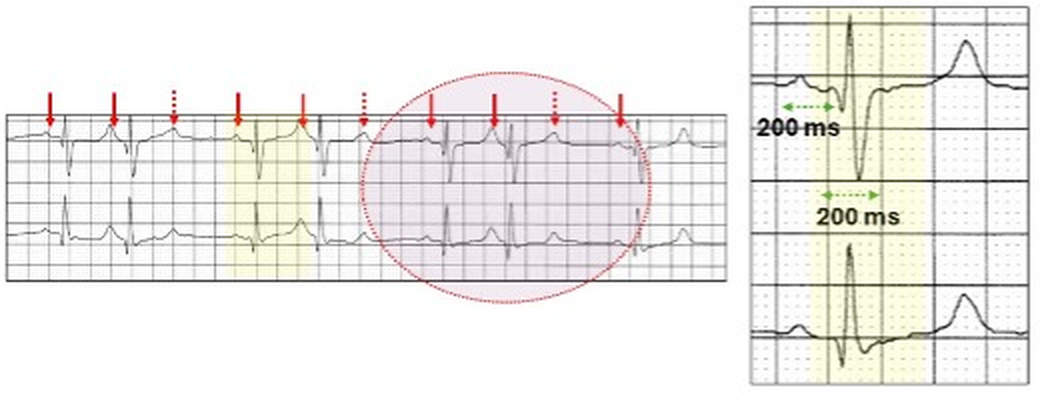
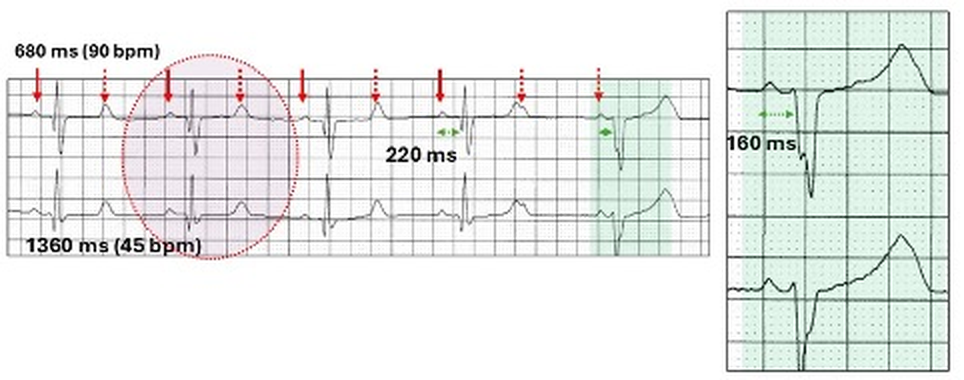
The rhythm is sinus with a broad QRS (yellow highlight). Every third beat is dropped (red stippled arrow) but PR prolongation cannot be determined. This is 3:2 second degree AV block (purple oval).
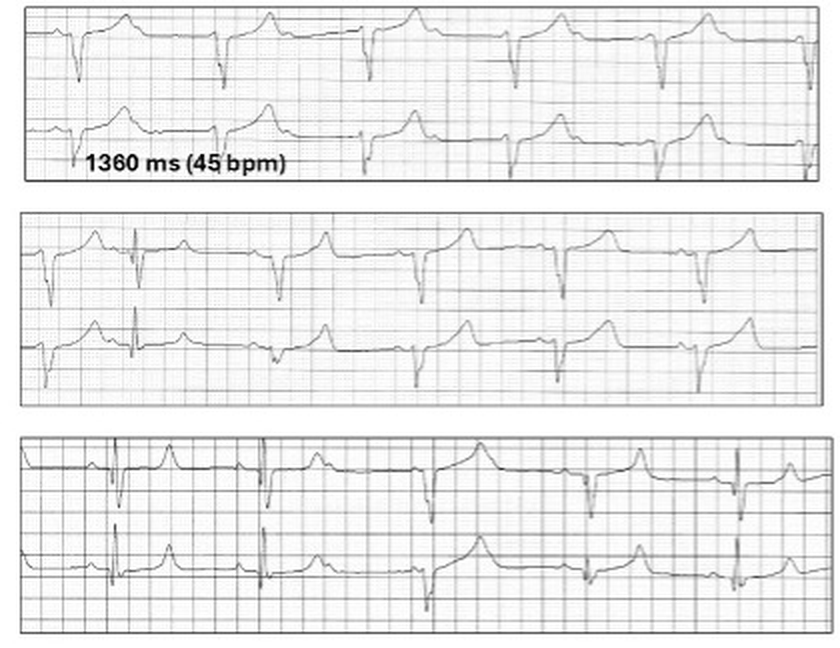
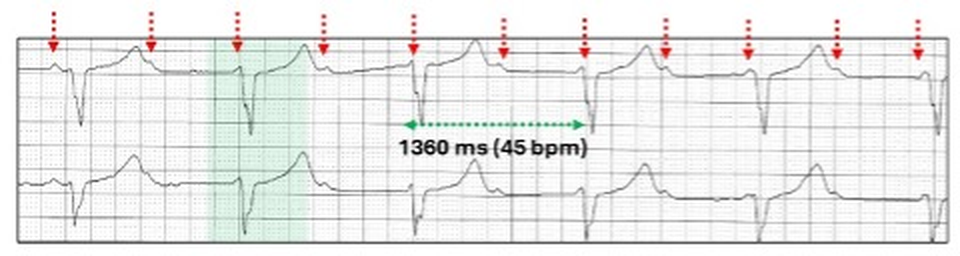
2:1 AV block at a ventricular rate of 45 bpm. Cannot differentiate between Wenckebach and type II AV block. At the end of the tracing, there is a QRS with a different morphology (green highlight). The PR interval is shorter.
In order to understand the signiicance of this beat, we need to review further tracings.
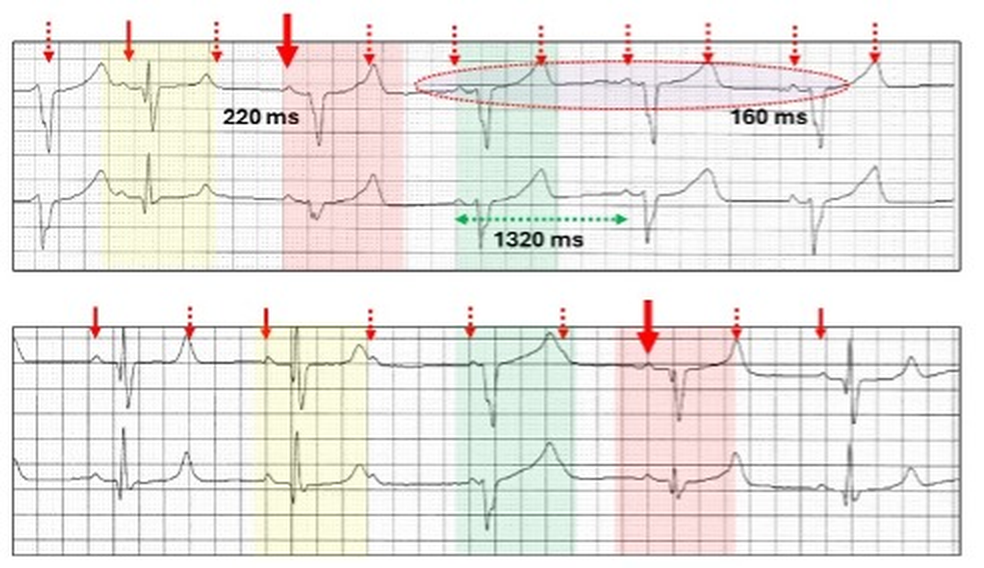
Complete AV block (red stippled arrows) with a broad QRS escape rhythm at a rate identical to the sinus generated rhythm (45 bpm).
The short PR interval in the previous tracing suggests that this was an escape beat and related to the complete AV block.
There are other QRS complexes with different QRS morphologies (red highlight).
Because the sinus generated and the ectopic QRS rhythms have a near identical rate, they compete with each other and fortuitiously P waves may be present before the ectopic beats (purple oval). Provided the PR interval is shorter than 200 ms (160 ms), then the sinus generated QRS is suppressed. With a longer PR interval (220 ms), conduction to the ventricle may occur (thick red arrows) resulting in fusion beats (red highlight) and these vary in configuration, depending on the contribution of each focus.
In summary: Sinus rhythm with conduction systen disease including
I was asked for a second opinion on this Holter study as there was confusion with different QRS configurations and rhythms. I selected a bunch of strips. What do you think?
As its name implies, AVNRT is a reentrant junctional or supraventricular tachyarrhythmia which involves the fast and slow pathways within the AV node creating a self-perpetuating circus movement. It can be divided into typical (slow-fast) or atypical (fast-slow) as well as several rarer forms related to more than one slow or fast pathway with similar electrophysiological properties. On the ECG, they can be identified and differentiated by the positioning of the P wave in relation to the QRS complex, which in turn is related to the direction of the re-entrant AV nodal circuit. However, in about 60% of cases, the P wave is buried in the QRS/T and cannot be identified on the surface ECG.
Retrograde conduction is defined as conduction from an ectopic site to the atrium via the AV node or accessory pathway and referred to as VA conduction. II results in a P wave configuration which differs from an anterograde P wave, and in most ECG leads is inverted. The site from where the impulse originates can be the AV node, Bundle of His, distal conducting system or the body of the ventricles including ventricular pacing. On the ECG, the QRS complex usually precedes the inverted retrograde P wave but on occasion may follow it.