To receive a free PDF copy of The Fundamentals of Electrocardiograph Interpretation by Harry Mond, subscribe to his email blog by entering your email address below.
Thank you! Your submission has been received!
Oops! Something went wrong while submitting the form.
Purchase the textbook
Purchase a hard cover or paperback copy of The Fundamentals of Electrocardiograph Interpretation by Harry Mond on Amazon.
In order to interpret the ECG, let us start by reviewing the ventricular ectopic.
In summary:
A ventricular ectopic has a
A premature wide QRS (red highlight) with no preceding P wave.
The QRS and T wave are discordant (T wave polarity opposite to the QRS).
Unless there is retrograde conduction to the atria, the sinus cycle is not interrupted (red vertical lines), but there is a concealed P wave embedded in the ectopic T wave (blue stippled line)
There is a compensatory pause (red horizontal arrow), because the concealed P wave does not conduct to the ventricle.
The relationship of the ventricular ectopic to the preceding sinus QRS is referred to as the coupling interval (blue horizontal arrow) and with more than one similar ventricular ectopic (unifocal) in the tracing, this interval usually remains constant.
Now, let us return to our ECG.
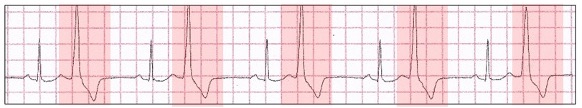
Sinus rhythm with ventricular ectopics every sixth beat (red highlight).
Ventricular hexageminy. Rarely reported in the literature, not necessarily because it is rare but rather long strips are required to make the diagnosis.
What bugs me is that some examples in the literature only have two ventricular ectopics (yellow highlight) with 5 sinus beats between (red highlight) and therefore we do not know if it is really a single sequence or a true run.
Therefore, In order to diagnose ventricular hexageminy, we require at least two sequences or three ectopics.
Let us review the various ventricular “geminy” groupings.
Ventricular bigeminy: Ventricular ectopic every second beat (red highlight).
Ventricular trigeminy: Ventricular ectopic every third beat (red highlight).
Ventricular quadrigeminy: Ventricular ectopic every fourth beat (red highlight}.
Ventricular pentageminy: Ventricular ectopic every fifth beat (red highlight).
Ventricular hexageminy: Ventricular ectopic every sixth beat (red highlight).
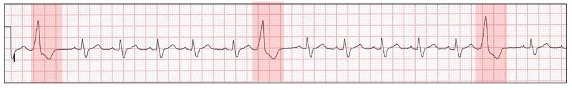
This ECG was reported as ventricular trigeminy with fusion.
What do you think?
There are two very late ventricular ectopics (red highlight) occurring after the P wave in the PR interval and are referred to as end diastolic. The next ventricular ectopic is later again (yellow highlight) and is fusion between the ventricular ectopic and the next sinus generated QRS. The coupling intervals differ and the ventricular ectopics have a fixed coupling interval between them. This is called ventricular parasystoleand is easily confused with “geminy”grouping.
Ventricular parasystole:
Rare ECG finding
An independent ventricular ectopic focus
Sinus impulses cannot enter and reset
Sinus impulses, can however, create refractoriness in the surrounding myocardium causing an exit block.
ECG features:
Unifocal ventricular ectopics
Variable coupling
Fixed, usually very slow inter-ectopic intervals
No ventricular ectopics during the refractory periods
Fusion beats are common depending on the timing.
Our tracing has all these criteria but to be absolutely sure, we need longer strips.
Here is another example which shows how difficult it is to confirm the diagnosis of ventricular parasystole.
Atrial fibrillation
The ventricular ectopics are unifocal (red highlight)
The coupling intervals differ, becoming shorter
The inter-ectopic intervals are fixed
The yellow highlight shows that the next ectopic falls in the refractory period of the intrinsic beat.
As its name implies, AVNRT is a reentrant junctional or supraventricular tachyarrhythmia which involves the fast and slow pathways within the AV node creating a self-perpetuating circus movement. It can be divided into typical (slow-fast) or atypical (fast-slow) as well as several rarer forms related to more than one slow or fast pathway with similar electrophysiological properties. On the ECG, they can be identified and differentiated by the positioning of the P wave in relation to the QRS complex, which in turn is related to the direction of the re-entrant AV nodal circuit. However, in about 60% of cases, the P wave is buried in the QRS/T and cannot be identified on the surface ECG.
Retrograde conduction is defined as conduction from an ectopic site to the atrium via the AV node or accessory pathway and referred to as VA conduction. II results in a P wave configuration which differs from an anterograde P wave, and in most ECG leads is inverted. The site from where the impulse originates can be the AV node, Bundle of His, distal conducting system or the body of the ventricles including ventricular pacing. On the ECG, the QRS complex usually precedes the inverted retrograde P wave but on occasion may follow it.
In 1970, I commenced work as a “novice” cardiologist at The Royal Melbourne Hospital. Training at that time was learning how to recognise the diastolic murmur of mitral stenosis and making sure the ECG and chest x-rays were the correct way up. As this was prior to coronary artery surgery, stenting and echocardiography, the ECG was a highly respected tool for the diagnosis of many conditions. I was fortunate to befriend a number of the gurus of ECG interpretation who taught me to look into the soul of an ECG. Today, even though the ECG is the first investigation performed by a cardiologist, the art of ECG interpretation has been lost because we depend on the new tools for cardiac diagnosis.